Glafabra
One treatment. Years of relief from Fabry disease.
Drug Development Pipeline (FDA)
Stage is computed from completed factual milestones. No timelines, target dates, or next milestones are shown.
| Program | Stage |
|---|---|
| GT-GLA-S03 Fabry disease · Autologous ex vivo lentiviral cell-based gene therapy (“Live-cel”) Modality: CGT Status: Active Regulatory: FDA Orphan Drug Designation | —— Completed milestone: — Completed: Development candidate nominated. Furthest Development: Phase I in Canada |
INVESTIGATIONAL NOTICE: GT-GLA-S03 has not been approved by the FDA. This page describes the company’s technology, development strategy, and business progress only.
One treatment. Years of relief from Fabry disease.
Glafabra Therapeutics is developing Live-cel™ — a long-acting, cell-based gene therapy designed to replace 5 years of biweekly infusions with a single durable treatment for Fabry disease. Over 5 years of published clinical data support the company’s approach.
5 Key Takeaways for Glafabra
A clinically grounded, patient-centered platform positioned for U.S. clinical advancement.
Clinically Grounded Lead Asset
The Fabry program has been tested in human clinical trials in Canada.
Multi-Year Effect from One Dose
Published clinical data support at least five years of enzyme activity after a single treatment.
Reduces Biweekly Infusion Burden
Live-cel™ is designed to reduce the need for recurring enzyme replacement infusions.
FDA Orphan Drug Designation
Received in March 2026, supporting the company’s rare disease development pathway.
U.S. Pathway Taking Shape
Clinical collaboration and IND-enabling work are intended to support U.S. clinical advancement.
What is Fabry disease?
For clinicians, patients, and investors alike, understanding the scope of this disease is the starting point for understanding why a better treatment matters.
For Healthcare Practitioners: Fabry disease is an X-linked lysosomal storage disorder caused by deficiency of alpha-galactosidase A, leading to progressive accumulation of globotriaosylceramide in vascular endothelium, cardiomyocytes, and renal tubular cells.
Fabry disease is a rare inherited disorder that can progressively damage the kidneys, heart, nervous system, and other organs. It can begin in childhood or appear later in adulthood, and it often goes undiagnosed for years.
In severe cases, Fabry disease can become life-threatening, leading to complications such as kidney failure, heart failure, or stroke. Yet even for patients receiving treatment, the experience is not easy. The current standard of care can require infusions every other week.
Over 5 years, biweekly Enzyme Replacement Therapy (ERT) may mean roughly 130 infusion cycles, creating a recurring treatment burden that can affect work, travel, family time, and quality of life.
- Kidney damage progressing to failure
- Cardiac complications including hypertrophic cardiomyopathy
- Stroke and cerebrovascular disease
- Chronic neuropathic pain
- Years of diagnostic delay for many patients
The burden of biweekly treatment
Patient experiences help illustrate why reducing treatment burden matters. These experiences are individual and may not be representative of all patients.
“I was still losing time with my family every two weeks to do the ERT.”
— Ryan, FACTS trial participant
“I definitely miss the freedom. I’m now back on a bi-weekly infusion schedule.”
— Ryan, FACTS trial participant
“Everyone’s goal ought to be to enjoy a long, healthy life.”
— Darren, FACTS trial participant
What this means for patients
Fabry patients receiving enzyme replacement therapy may need to plan life around recurring infusions, medication delivery, travel limitations, and time away from family or work.
Glafabra’s Live-cel™ approach is being developed to reduce that recurring burden by supporting durable enzyme production from a patient’s own modified cells.
A single durable treatment designed to replace 5 years of biweekly infusions for Fabry disease.
Clinical Foundation
Glafabra’s story begins with real patients, real data, and peer-reviewed results — not just preclinical promise.
Members of the founding team conducted clinical trials in Canada that provide the scientific and clinical foundation for the company’s next stage of U.S. development. The key finding described by the company is at least five years of sustained effect after a single infusion of the cell-based therapy.
In the referenced trial, patients were initially on standard ERT. When ERT was stopped, toxic metabolite levels rose by 41%. Following a single dose of cell therapy, metabolite levels dropped 48% — to a level below where patients started on ERT. That lower level was maintained at the five-year follow-up.
Company-referenced publication: PMID 39794302.
Why this data matters to clinicians
- May reduce the logistical and adherence challenges of recurring ERT
- Potentially slows or prevents end-organ damage progression
- May address CNS manifestations that are difficult for ERT and AAV approaches to reach
- May be repeatable if clinically indicated
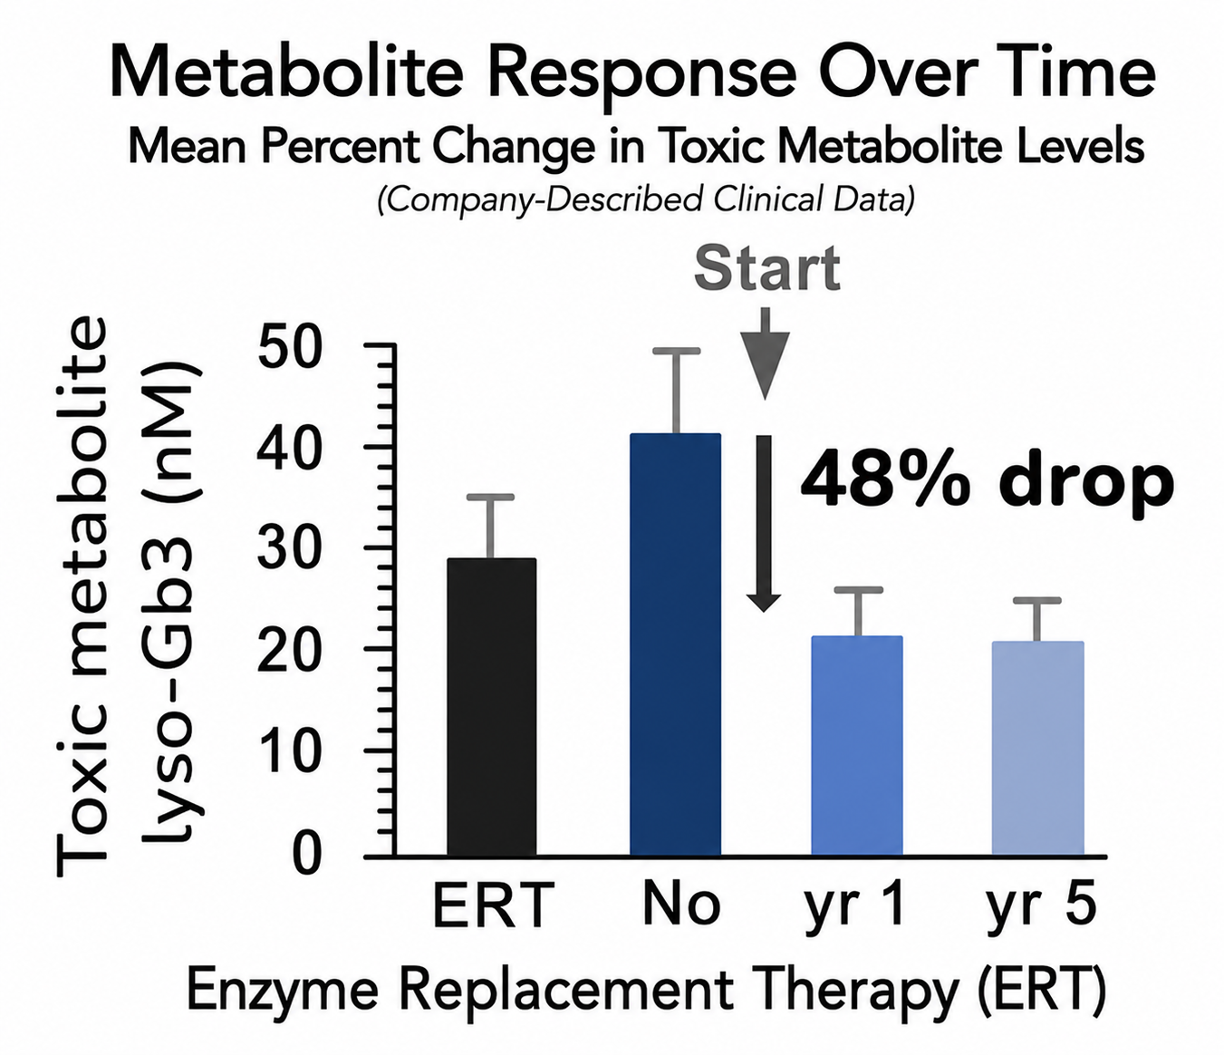
Illustrative representation based on company-described clinical data. See PMID 39794302 for full data.
Clinical Development Timeline
Phase I Clinical Trial
Co-founders conducted first-in-human trial of the Live-cel approach in Fabry disease patients.
5-Year Follow-Up Published
Peer-reviewed publication confirming sustained enzyme activity and safety at five years post-treatment.
Glafabra Therapeutics Founded
Drs. Hopkins, Medin, and Foley founded Glafabra to bring the Live-cel platform to U.S. clinical development.
University of Utah Collaboration
Announced intent to partner with U of U Health, Utah DCC, and CellReGen for U.S. clinical development.
FDA Orphan Drug Designation
GT-GLA-S03 received FDA Orphan Drug Designation — a key regulatory validation milestone.
U.S. Phase II Clinical Trial
Planned IND filing and first patient enrollment at University of Utah Health.
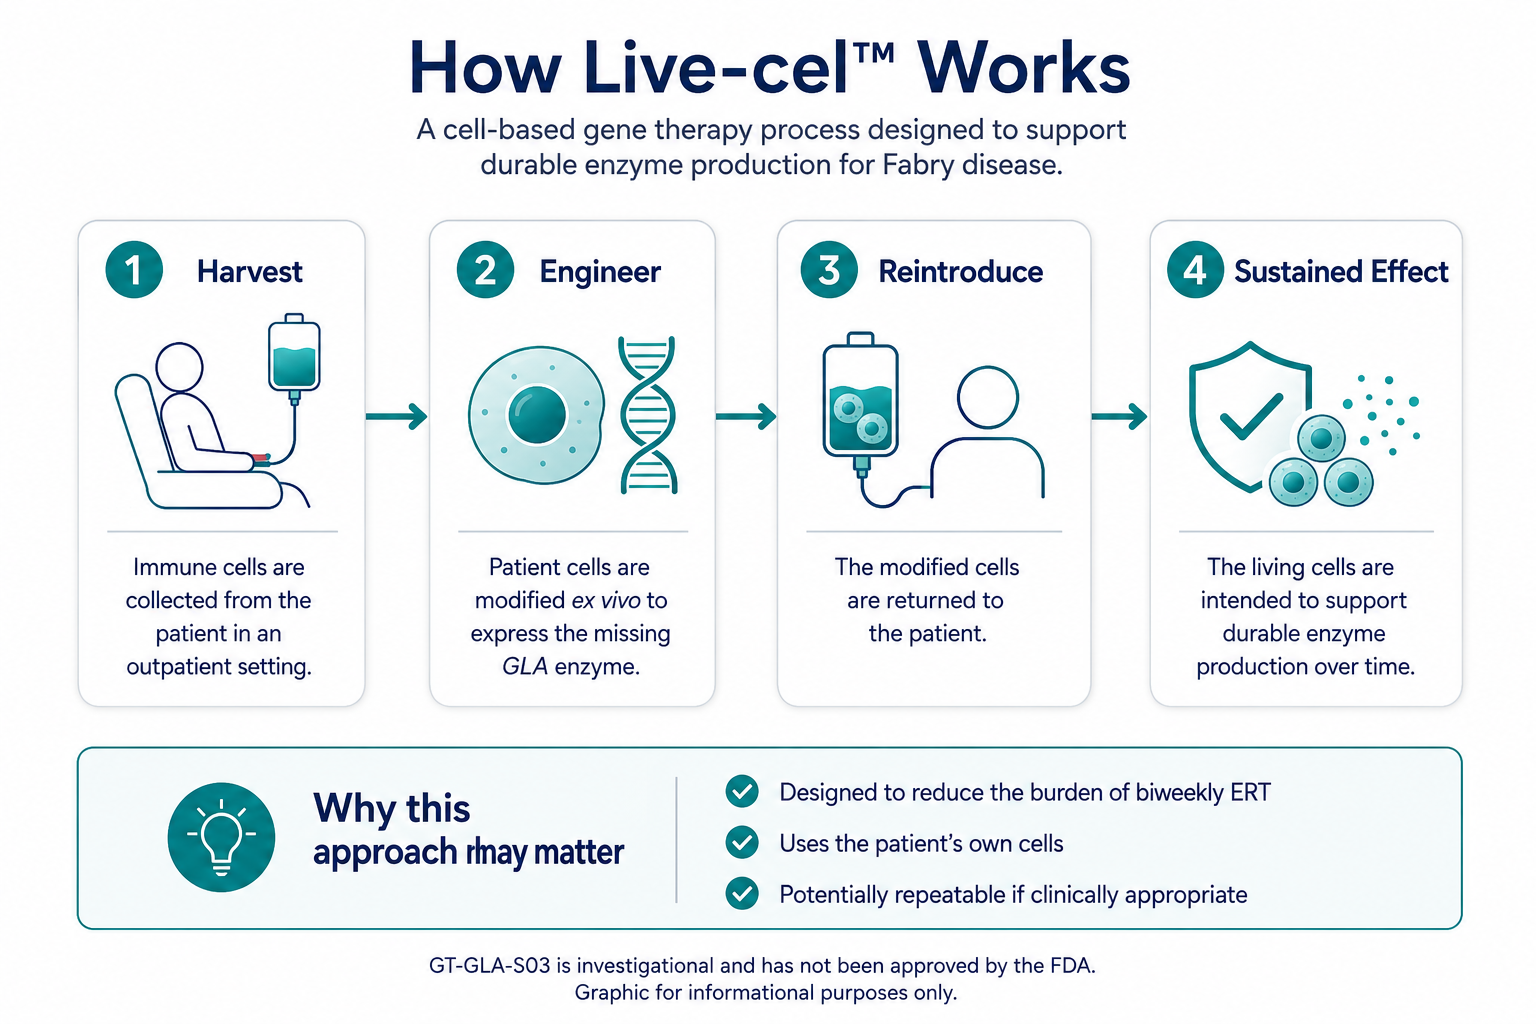
The platform uses a patient’s own cells as a living, durable source of enzyme production — without viral vectors or repeated infusions.
FDA Orphan Drug Designation — March 2026
In March 2026, GT-GLA-S03 received FDA Orphan Drug Designation for Fabry disease. This designation supports the development pathway for the lead asset and may provide economic and strategic advantages as the company moves toward U.S. clinical advancement.
Why Live-cel™ Stands Apart
Compared to enzyme replacement therapy and AAV-based gene therapy approaches, the company believes its platform offers a distinct clinical and commercial profile.
Long Duration
One treatment demonstrated maintained enzyme activity at five-year follow-up in the referenced clinical work.
Large Effect
Cell therapy reduced toxic metabolites below the ERT-treated baseline described by the company.
Repeatable
The company believes Live-cel™ may be administered again if clinically appropriate.
Potential CNS Access
Glafabra believes the cellular approach may help address manifestations that are difficult for ERT and AAV approaches to reach.
Lower Burden Procedure
Treatment is designed for an outpatient setting without hospitalization or intensive conditioning.
Potential Cost Advantage
The company models its approach as lower cost than the current annual standard of care.
An Existing, Growing, Commercially-Validated Market
The ERT market for Fabry, Gaucher, and Pompe disease is already established and growing at low-double-digit rates annually - validated by four publicly traded companies currently generating revenue. Live-cel™ is designed to serve these same patients with a better treatment, not to create demand from scratch.
Market sizing based on publicly reported net sales from Sanofi, Takeda, and Amicus Therapeutics (2024 filings). Gaucher and Pompe figures from third-party market reports (Grand View Research, DelveInsight). Platform ceiling is a theoretical maximum assuming full diagnosis and ERT-equivalent pricing across ~2M global patients.
Use of Proceeds
Proceeds are intended to support the milestones required to advance GT-GLA-S03 toward a U.S. IND filing and Phase II trial initiation.
Key Milestones on the Path to First Patient Enrolled
Three critical steps between now and U.S. Phase II trial initiation.
IND-Enabling Work & FDA INTERACT Meeting - scheduled for July 16, 2026
Complete IND-enabling studies and align with FDA on the clinical development pathway.
Open IND Filing
Submit Investigational New Drug application to FDA with clinical and operational support.
First Patient Enrolled — U.S. Trial
Initiate Phase II efficacy trial, a potential value inflection point for partnership or acquisition interest.
The Team
The leadership combines rare disease science, clinical development, regulatory strategy, manufacturing, and company-building experience.

Dr. Chris Hopkins, PhD, MBA
Chief Executive Officer
Scientist and entrepreneur; co-founded Glafabra based on the Canadian clinical trial results.

Elizabeth Wagner
Chief Operating Officer
Life science executive with experience working across CROs, academic partners, and manufacturers.

Sidney Norton, MBA
Acting Chief Financial Officer
Healthcare executive with 25 years of experience; currently CFO of Intermountain Primary Children's Hospitals.

Dr. Jeffrey Medin, PhD
Founder and Chief Scientific Officer
Cell and gene therapy pioneer; co-founded NASDAQ-traded rare disease company Avrobio, Inc.

Dr. Ronan Foley, MD
Founder and Chief Medical Officer
Clinical hematologist and Professor at McMaster University; Director of the Clinical Stem Cell Laboratory at Juravinski Hospital.

Dr. Krista Casazza
Director of Regulatory Science
Regulatory science leader with experience in biomarker discovery and lysosomal storage disorders.

Dr. Kevin Marhenke, Pharm.D.
Director of Medical Affairs
Four decades in pharma and biotech; led market introduction of Enbrel, Prolia, and EVENITY at Amgen.

Dr. Tetsu Yung, PhD, MBA
Director of APAC Strategies
20+ years of R&D experience spanning Eisai and Fortrea Japan; fluent in five languages.
Built for U.S. Execution
The company is building an operational ecosystem around its Fabry program.

University of Utah / Utah DCC / CellReGen
Supporting clinical trial management, data coordination, pharmacovigilance, manufacturing, technology transfer, and IND preparation.

Rogue Funds
Lead investor in the company’s pre-seed financing round, according to the issuer.

FDA Orphan Drug Designation
Received March 2026, strengthening the company’s rare disease development pathway.
Beyond Fabry: A Platform for Enzyme Deficiency Disorders
Fabry disease is the lead indication, but not the endpoint. The Live-cel™ platform is designed to address a broader set of enzyme deficiency disorders.
Fabry Disease Clinical Stage
Deficiency in alpha-galactosidase A. Lead program with five years of clinical follow-up data and FDA Orphan Drug Designation.
Pompe Disease Pipeline
Deficiency in acid alpha-glucosidase (GAA). Pipeline opportunity leveraging the same Live-cel manufacturing and delivery approach.
Gaucher Disease Pipeline
Deficiency in glucocerebrosidase (GBA1). Part of a broader platform vision for enzyme deficiency disorders.
Abbreviations
AAV — Adeno-Associated Virus CMC — Chemistry, Manufacturing, and Controls CNS — Central Nervous System DCC — Data Coordinating Center ERT — Enzyme Replacement Therapy G&A — General & Administrative IND — Investigational New Drug
Important: We are considering a capital raise and are “Testing the Waters” under Regulation Crowdfunding. No money or other consideration is being solicited, and any that is sent in response will not be accepted. We cannot accept any offer to buy securities, and no part of the purchase price can be received, until the offering statement is filed and only through the BioTech Funding Portal platform. Submitting an indication of interest via the “Express Interest” button on this page involves no obligation or commitment of any kind.
Q&A

Glafabra posted: Meet Dr. Michael Bennett: Acting Chief Business Officer
Dr. Michael Bennett joined Glafabra in October as Acting Chief Business Officer, leading partnering and business development for the Live-cel platform, including the search for a manufacturing partner.
Most recently he was VP, Corporate Liaison at Kyowa Kirin. Before that, he was Director of Business Development at the Cell and Gene Therapy Catapult, where he headed the BD, IP and legal teams, and

Glafabra posted: Month Four: Where the Program Stands
Since the last update (Sep 7): co-founder Dr. Jeff Medin presented the FACTS data at IFFD 2026 in Tokyo (Oct 2), putting it in front of the Fabry specialist community; the team took part in BIO Japan in Yokohama (Oct 7-9) to meet manufacturing and Japan-based partners; and this channel has walked through the program's key diligence questions: the biomarker and kidney endpoints FDA recommended, the

Glafabra posted: What Is the U.S. Phase 1/2 Trial Designed to Answer?
The planned U.S. Phase 1/2 trial is designed to measure alpha-Gal A enzyme activity, plasma lyso-Gb3, and eGFR slope, the same readouts FDA emphasized in its INTERACT feedback. University of Utah Health is planned to be a clinical site. Current planning targets an IND in mid-2027 and first patient enrolled in H1 2028, with a 12-month data readout in 2029.
Interpretation: The core question is wheth

Glafabra posted: Pompe and Gaucher: What 'Preclinical' Means for Programs Two and Three
GT-GAA-S04 (Pompe) is preclinical, with efficacy demonstrated in animal models. GT-GBA1-S05 (Gaucher) is in preclinical development in animal models. Both apply the same Live-cel approach as the Fabry program: a patient's own stem cells, corrected with a working copy of the relevant gene (GAA or GBA1).
Interpretation: The value of the two later programs today is platform leverage: shared vector, p

Glafabra posted: Why Does an Autologous Therapy Need a Closed, Automated Manufacturing Process?
Every Live-cel dose starts with the patient's own stem cells, so each batch is made for one person. FDA's INTERACT feedback identified finalizing potency assays and release specifications, and running a GMP manufacturing campaign under a closed process, as remaining work before an IND. FDA also confirmed CMC knowledge (vector backbone, packaging system, process steps) can be leveraged across our F

Glafabra posted: Orphan Drug Designation and RMAT: What Each Does, and Doesn't, Mean
GT-GLA-S03 holds FDA Orphan Drug Designation, which recognizes Fabry as a rare disease and provides development incentives, including potential market exclusivity if the product is approved. RMAT (Regenerative Medicine Advanced Therapy) designation is separate: it requires preliminary clinical evidence that a regenerative therapy may address an unmet need in a serious condition. Our current plan t

Glafabra posted: Where Would Live-cel Fit Among Today's Fabry Treatments?
Enzyme replacement therapy is the standard of care: an IV infusion about every two weeks, for life. Roughly 40% of ERT patients develop anti-drug antibodies over time, which can reduce its effectiveness, and ERT does not fully reach every tissue, notably the heart and nervous system. Oral chaperone therapy (migalastat) works only for the roughly 35-50% of patients with an amenable GLA variant. AAV

Glafabra posted: Meet Dr. Ronan Foley, MD: Co-Founder and Transplant Specialist
Dr. Ronan Foley, MD, is a Co-Founder of Glafabra and a transplant specialist.
With co-founder Dr. Jeffrey Medin, he co-led the Canadian FACTS trial (NCT02800070), which followed five Fabry patients for five years, including the non-myeloablative, melphalan-based conditioning that allowed 4 of 5 patients to go home the same day.
For diligence purposes: the clinician who led the pilot study's transp

Glafabra posted: What Are the Known Risks of Lentiviral Stem Cell Gene Therapy?
The main recognized risks of lentiviral HSC gene therapy are (1) insertional risk: the vector integrates into the genome, and in rare cases in the wider field, integration has been linked to abnormal cell growth; (2) conditioning risk: the chemotherapy used to make room for corrected cells carries its own side effects; and (3) procedure risk from stem cell collection and re-infusion. In FACTS, ins

Glafabra posted: Is There a Cure for Fabry Disease?
here is currently no approved cure for Fabry disease. Approved treatments, enzyme replacement therapy (an IV infusion about every two weeks) and, for patients with an amenable GLA variant, an oral chaperone (migalastat), manage the disease. Several gene therapy approaches aiming for durable enzyme production are in clinical development.
Interpretation: Live-cel (GT-GLA-S03) is one of those approac

Proposed Raise: $1M (SAFE: 20% discount + $12M Cap)
We are considering a capital raise and are “Testing the Waters” under Regulation Crowdfunding. No money or other consideration is being solicited, and any that is sent in response will not be accepted. We cannot accept any offer to buy securities, and no part of the purchase price can be received, until the offering statement is filed and only through the BioTech Funding Portal. Submitting an indication of interest via the “Express Interest” button on this page involves no obligation or commitment of any kind.
